Why Bending Over a Low Bed Costs Tall Nurses More Than Lifting Does
Quick Answer: A sustained forward lean loads the lumbar spine continuously, while a lift loads it briefly. Standard bed and workstation heights sit well below a tall nurse’s optimal working height, so a 12-hour shift accumulates hours of static flexion. Adjusting bed height every single time is the fix, and it takes four seconds.
You are careful about lifting. You use the mechanical aids, you get help, you bend your knees.
And your lower back still aches by hour eight — on days with no heavy transfers at all.
The damage is not in the lifts. It is in the leaning.


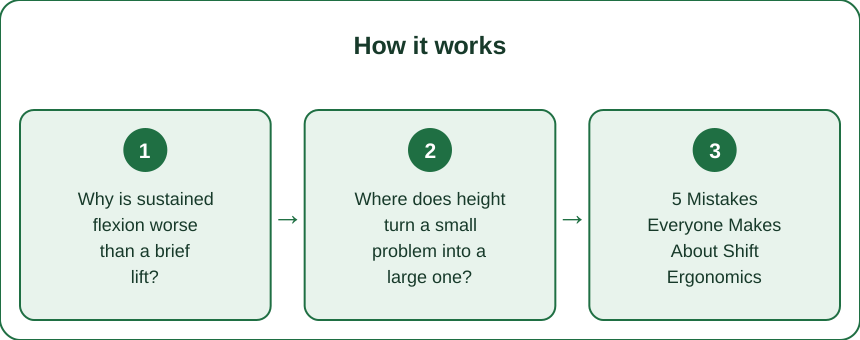
Why is sustained flexion worse than a brief lift?
A heavy lift produces a large load for 1 to 3 seconds. A forward lean produces a moderate load continuously, for minutes at a time, dozens of times a shift.
Leaning forward just 20 degrees without support increases compressive load on the lumbar discs substantially compared to standing upright — the upper body’s weight is now cantilevered forward, and the spinal erectors must counterbalance it the entire time.
Muscles under sustained isometric contraction fatigue and lose their ability to protect the joint. Once the erectors tire, more load transfers to passive structures: ligaments, discs, and facet joints. That is the mechanism behind the specific end-of-shift ache most nurses describe — dull, central, and worse after standing still.
And exposure is high. Time-motion observations of clinical work consistently find substantial portions of a shift spent in trunk flexion. Small angle, long duration, many repetitions.
Where does height turn a small problem into a large one?
Optimal working height for precision tasks is roughly elbow height minus 2 to 4 inches. For a nurse who is 5’4”, that lands around 37 to 39 inches. For a nurse who is 6’0”, it is closer to 43 to 45 inches.
Hospital beds typically adjust between 15 and 30 inches at the mattress platform, plus mattress thickness. Fully raised, many still leave a tall clinician working 4 to 8 inches below optimal.
Everything else in the environment has the same bias. Computer carts, med prep counters, sinks, and phlebotomy chairs are all specified around a mid-range user.
So the tall nurse does not have one badly sized station. They have a whole shift of them, each requiring a few degrees of lean that a shorter colleague does not need. It compounds invisibly, because no individual moment feels like a problem.
5 Mistakes Everyone Makes About Shift Ergonomics
1. Adjusting the bed only for big tasks. Most nurses raise the bed for a transfer and not for a dressing change, an IV start, or charting at the bedside — which is where the minutes actually accumulate.
2. Leaning on the rail instead of raising the bed. Bracing on the rail relieves the arms but keeps the spine flexed and adds a twist. It feels better and is not.
3. Widening the stance instead of getting closer. Distance from the work is the main variable. A step closer beats any stance adjustment.
4. Saving stretching for after the shift. A 30 second standing extension between rooms does more than fifteen minutes at 8pm, because it interrupts the sustained load rather than treating the aftermath.
5. Assuming shoes fix back pain. Good footwear helps foot and knee fatigue significantly and does very little for lumbar flexion load. Buy the shoes and still raise the bed.

What does a realistic four-second habit look like?
The intervention that works is not a program. It is a trigger tied to something you already do.
Rule: hand on the bed control before hand on the patient. Every single time, for every task longer than about ten seconds. Raise to just below your elbow height, work, and lower it again before you leave. Four seconds each way.
Set the computer cart once per shift, not per use. Find your height, note where the pole clamp sits, and reset it every time someone shorter has borrowed it.
Kneel for genuinely low work. Foot care, low lines, floor-level equipment — one knee down keeps your spine neutral and costs nothing but a knee on a clean surface.
Use the chair. For anything seated-appropriate that takes more than two minutes, sitting at the right height beats standing bent over. Nurses skip this out of urgency habit more than necessity.
Batch bedside charting. Standing bent at a low surface entering notes is the highest-duration flexion task most nurses do. Chart at a properly set cart, standing tall.
What builds tolerance when the environment cannot change?
You cannot re-specify hospital furniture. You can build a spine that tolerates the exposure better.
Back extensor endurance is the specific quality. Research on occupational low back pain consistently identifies extensor endurance — not strength — as the protective factor. Prone back extension holds, starting at 20 seconds and building toward 60, three times a week, target exactly this.
Hip hinge patterning. Practice the hinge with a dowel along your spine until bending from the hips rather than the lower back is automatic. Ten reps daily for two weeks changes the default.
Hip flexor and hamstring mobility. Tight hips force the lumbar spine to make up the difference in every forward reach. Two 30 second stretches per side, daily.
Anti-rotation work. Pallof presses, 10 reps per side twice a week. Most bedside tasks are asymmetric, and rotation under flexion is the least tolerated combination.
This is general information, not medical advice. Back pain that radiates into a leg, involves numbness or weakness, or does not settle with rest and pattern change should be evaluated — and occupational health exists partly for this.
FAQ: Tall Nurse Ergonomics Questions, Answered
Are compression socks worth it for back pain?
They help leg fatigue and swelling over a 12-hour shift, which indirectly helps how you stand late in the day. They do nothing directly for lumbar load — useful, but not the fix.
What if the bed does not go high enough even at maximum?
Then kneel, sit, or use a small step for the patient side rather than accepting the lean. Also report it — bed replacement cycles do respond to documented staff injury risk, and a tall clinician raising it is doing the whole unit a favor.
Does one long shift do more harm than two short ones?
Cumulative flexion time matters more than shift structure, but fatigue means the last hours of a 12 are the highest-risk window. Front-load the physically demanding tasks when you can.
TL;DR:
- Sustained forward lean loads the lumbar spine continuously; a lift loads it for seconds.
- Standard bed and cart heights leave tall clinicians working 4–8 inches below optimal.
- Raise the bed for every task, not just transfers — four seconds each way.
- Build back extensor endurance rather than strength; it is the protective quality for this exposure.
The lifts you are already careful about were never your main exposure. The unremarkable lean over a bed that was six inches too low, repeated forty times a shift, is what your back has been quietly paying for.
Keep Reading
This article is for general informational and styling purposes only. Fit, sizing, and product availability may vary.
